Skip to main content
Atlas · Foot

Quadratus plantae

Quadratus plantae lies in the second plantar layer, beneath flexor digitorum brevis. It links the calcaneus to the long toe-flexor tendon and helps bend the smaller toes. Its deep position makes confident surface isolation difficult; plantar heel pain should not be attributed to it from tenderness alone.

Quadratus plantae
Body region
Foot
Reference type
Anatomy & examination
Trigger-point map not yet documented
Common symptoms
3
patterns cataloged
Contributors
2
Factors to assess

Muscle overview

Symptoms and first steps

Practical first steps

  • Keep the toes moving comfortably without forcing the painful direction.
  • Choose tolerable activity and shoes that do not compress the painful area.
  • Record the task and exact location that provoke symptoms to guide assessment.

When to seek assessment

  • Persistent focal bone pain or inability to bear weight after injury needs prompt assessment.
  • Progressive numbness, weakness or toe deformity warrants clinical review.

Quadratus plantae acts through flexor digitorum longus. A toe-flexion task tests the combined system, not this deep muscle alone.

Examination, palpation and treatment evidence

Illustrated overview

Quadratus Plantae · Anatomy

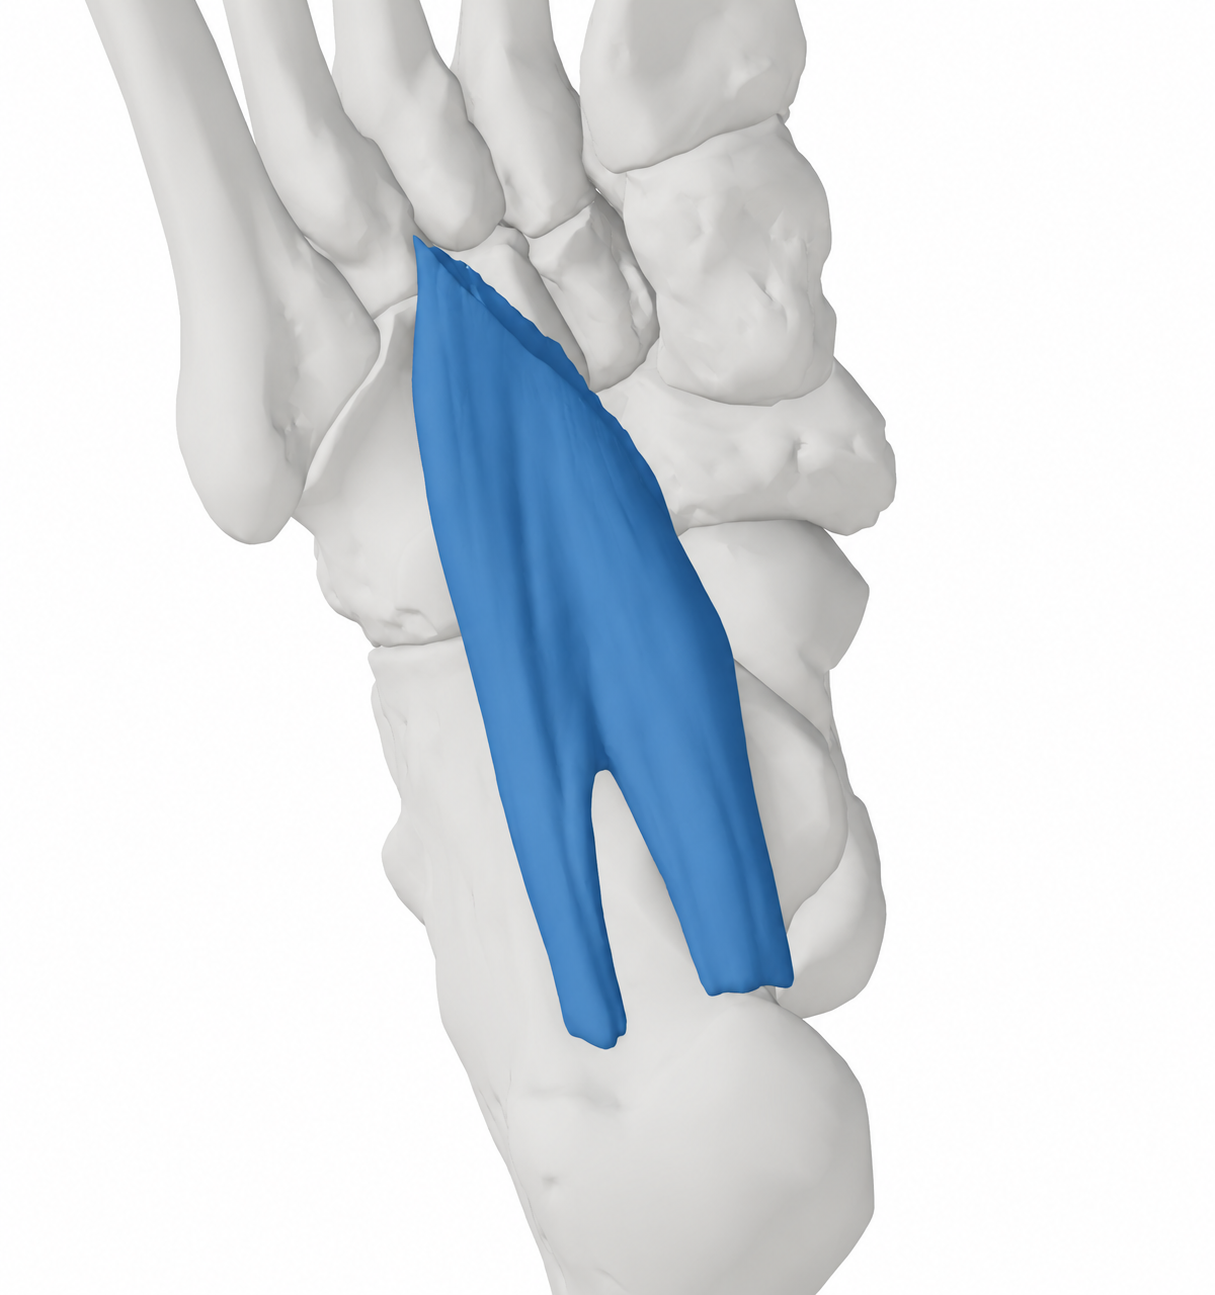
Right quadratus plantae with the source skeletal context. Source model rendered and material restyled; blue identifies the model structure, including its tendon-like continuations.

BodyParts3D, © The Database Center for Life Science. Adapted by MyofascialPain: source model rendered and material restyled. · CC BY-SA 2.1 Japan

Open full-size image
Browse related exercises (2)

Symptoms patients report

Discomfort around the heel and arch This is a regional complaint for assessment, not a characteristic referred-pain pattern from this muscle.

Difficulty with toe movement or push-off Pain, joint restriction and several muscles can affect the same task; note the location and activity rather than inferring a single-muscle cause.

Burning, numbness or focal swelling These findings direct attention to nerve or structural causes and should not be relabeled as muscle referral.

Contributors to assess

Changed activity or footwear demand Record recent changes in walking, running and shoe pressure; this history does not establish a muscle lesion.

Coexisting foot or toe disorder Joint alignment, plantar fascia, nerve and bone findings can alter loading and need their own assessment.

For clinicians and supervised training

Clinical reference

Anatomy and clinical examination reference. No muscle-specific trigger-point coordinates or referred-pain map have been verified for this entry.

Anatomy and palpation

Anatomical relationships

The medial head arises from the concave medial calcaneus below the flexor hallucis longus groove; the lateral head arises from the inferior-lateral calcaneus and long plantar ligament. They join the flexor digitorum longus tendon. The muscle assists flexion of toes 2–5 and receives the lateral plantar nerve.[1][2][3]

  • Second plantar layer beneath FDB
  • Medial and inferior-lateral calcaneal origins
  • Flexor digitorum longus tendon in the sole

Nearby structures. The long toe-flexor tendons, lumbricals and lateral plantar neurovascular structures share this deep region; calcaneal bone and plantar fascia require separate assessment.

Palpation

Patient position. Seated or lying with the foot supported and the plantar surface accessible.

Find the landmarks

  • Second plantar layer beneath FDB
  • Medial and inferior-lateral calcaneal origins
  • Flexor digitorum longus tendon in the sole

Examination sequence

  1. Start with the history, skin inspection and the person pointing to the painful region.
  2. Use light regional contact and compare with comfortable toe movement; record familiar pain without trying to force a deep structure into isolation.

Document the findings

  • Describe the actual tender region and any associated joint, skin or sensory finding.
  • Surface tenderness alone cannot confirm an individual intrinsic muscle as the pain source.

Limits and precautions

  • Avoid sustained deep pressure over painful bone, swollen joints or an area producing tingling.
  • Deep muscle layers and nearby plantar nerves limit surface localization; an anatomical diagram is not a procedural guide.
[1][2][3][8][9][5]

Examination and tests

2

Lesser-toe flexor-system loading[1][2][3][4]

Observe toe control and locate familiar discomfort during a low-load movement.

Position
Seated, with the heel supported and the foot relaxed; compare with the other side.
Technique
Gently bend toes 2–5 while keeping the foot supported, then relax. Compare comfortable movement and symptoms with the other foot; resistance is unnecessary when pain is present.
Positive finding
Record restricted movement, a side-to-side difference or familiar pain; there is no diagnostic positive cutoff.
Interpretation
The result helps choose tolerable movement practice and directs a broader foot assessment.
Limitations
The task cannot separate quadratus plantae from FDL, FDB or the other intrinsic muscles. This is an anatomy-informed task, not a validated trigger-point test.

Regional foot examination and symptom localization[8][9][5]

Distinguish muscle-region sensitivity from nerve, bone and joint findings around the heel and arch.

Position
Seated for inspection and gentle joint movement; assess walking only if weight bearing is comfortable.
Technique
Ask the person to indicate the painful area. Inspect skin and toe alignment, compare toe-joint motion and sensation, and identify whether tenderness is over bone, a joint, a web space or broader soft tissue.
Positive finding
Focal bone pain, sensory changes, joint swelling, altered toe alignment or a reproducible functional limitation.
Interpretation
Use the pattern to select the appropriate differential assessment; imaging depends on the history and findings.
Limitations
A tender region cannot identify one deep intrinsic muscle or exclude a structural injury. Do not repeatedly provoke painful compression.

Distinguishing other causes

Plantar fasciitis[8]

Findings that matter. Pain near the plantar heel, often most noticeable on the first steps after rest.

Next step. Assess plantar fascia and ankle mobility and use a diagnosis-specific plan.

Calcaneal or other foot stress injury[5]

Findings that matter. Focal bone pain with loading, particularly after an activity increase.

Next step. Reduce impact and arrange assessment; an early normal radiograph does not exclude stress injury.

Tibial or plantar nerve compression[9]

Findings that matter. Plantar burning, tingling, numbness or weakness.

Next step. Perform a neurological assessment and consider the tarsal tunnel and plantar nerve course.

Treatment selection and progression

Self-care and activity

Adjust provoking load and footwear[7][5]

Consider when. Nonurgent symptoms while the painful tissue and tolerable activity level are being assessed.

Reduce the activity or shoe pressure that consistently provokes symptoms. Keep comfortable walking and choose shoes that accommodate the foot and toes.

Dose and review
Base exposure on walking comfort and the response later that day; no isolated-muscle schedule is established.
Progression
Reintroduce the provoking activity gradually once ordinary walking is comfortable.
Stop or reassess
New swelling, persistent focal bone pain or increasing numbness calls for reassessment.
Evidence and limits
Regional foot-care advice. It does not show that one intrinsic muscle is the cause of pain.

Exercise and rehabilitation

Comfortable toe and foot-control practice[4][1][2][3]

Consider when. A stable, assessed foot presentation without a suspected fracture or unstable painful joint.

Use comfortable short-foot practice and controlled lesser-toe movement without prolonged gripping. Treat these as coordinated foot tasks rather than selective quadratus-plantae exercises.

Dose and review
Use a brief, comfortable practice period chosen for current control and symptoms. No validated isolated-muscle pain-treatment dose is available from the cited activation study.
Progression
Improve controlled movement first; add standing demand or resistance with a clinician when appropriate.
Stop or reassess
Stop for sharp pain, cramping that persists after relaxing, new tingling or worsening walking comfort.
Evidence and limits
The laboratory study demonstrates recruitment across intrinsic foot muscles. It does not demonstrate symptom relief or selective strengthening of this muscle.

Clinician-delivered care

Treat the established regional diagnosis[7][8][9][5]

Consider when. Persistent symptoms or examination findings suggesting a coexisting fascia, joint, nerve or bone disorder.

A clinician checks fascia, bone and nerves, then selects exercise and manual care. For confirmed plantar fasciitis, selected dry needling or low-level laser therapy (LLLT) may be discussed; LLLT is distinct from high-intensity laser (HILT). Persistent plantar fasciitis despite initial care may warrant a shockwave discussion and review of walking comfort.

Dose and review
Match treatment and review timing to the actual diagnosis and functional goal; no muscle-specific procedure course is established here.
Progression
Recheck the original walking or toe task before adding treatments.
Stop or reassess
Reassess progressive deformity, neurological change or failure to regain comfortable everyday loading.
Evidence and limits
Diagnosis-specific foot guidance; this entry does not extrapolate its benefits to an unconfirmed intrinsic-muscle trigger point.
Reassessment and follow-up

  • Repeat the same comfortable toe movement and walking task.
  • Track pain location, sensation and any swelling or change in toe alignment.
  • Revisit the diagnosis if the response does not fit the planned regional care.

Evidence and sources

  1. Anatomy, Bony Pelvis and Lower Limb, Foot Muscles

    2025 · Anatomy reference

    Card and Bordoni; updated December 9, 2025, checked October 11, 2026. Used for named muscles, attachments, actions and innervation. It does not validate isolated palpation or a trigger-point map. No illustration reproduced.

  2. Texas Tech University Health Sciences Center El Paso: Anatomy Tables — Leg and Foot

    2026 · University anatomy teaching reference

    Undated teaching table; year records October 2026 verification. Corroborates adductor hallucis and dorsal/plantar interosseous attachments, the second-toe movement axis and plantar nerve supply. No atlas illustration reproduced.

  3. Ultrasound of the plantar foot: a guide for the assessment of plantar intrinsic muscles

    2023 · Peer-reviewed anatomical imaging guide

    Zaottini and colleagues. Describes the layered anatomy and ultrasound identification of plantar intrinsic muscles, including the two heads of quadratus plantae. Imaging anatomy is not proof of a painful muscle or a validated surface palpation test.

  4. Intrinsic Foot Muscle Activation During Specific Exercises: A T2 Time Magnetic Resonance Imaging Study

    2016 · Descriptive laboratory study

    Eight collegiate athletes performed foot-control exercises. MRI assessed several muscles, including FDB, quadratus plantae and the oblique adductor hallucis; interossei and lumbricals were analyzed together. Activation does not establish pain relief, isolation of a muscle or a clinical dose.

  5. AAOS OrthoInfo: Stress Fractures of the Foot and Ankle

    2026 · Professional society clinical information

    Online page checked October 2026; year records verification. Load-related focal bone pain, reduced impact and diagnostic assessment; early radiographs may be unrevealing.

  6. Comparing two dry needling interventions for plantar heel pain: a randomised controlled trial

    2020 · Randomized active-comparator trial

    Al-Boloushi and colleagues; 102 enrolled; 68 completed 52-week follow-up. FDB and quadratus plantae were among several eligible muscles. Both groups also stretched. This establishes clinical-study coverage, not isolated-muscle efficacy, a validated referral contour or superiority to sham/no treatment.

  7. Heel Pain — Plantar Fasciitis: Revision 2023

    2023 · Clinical practice guideline

    APTA orthopedic and sports physical therapy guideline. Supports foot/ankle resistance exercise and plantar fascia/calf stretching for diagnosed plantar fasciitis. These are regional recommendations, not an FDB or quadratus-plantae MPS protocol.

  8. AAOS OrthoInfo: Plantar Fasciitis and Bone Spurs

    2026 · Professional society clinical information

    Online page checked October 2026; year records verification. Supports regional symptom assessment and conservative plantar-fascia care, not a muscle-specific diagnosis.

  9. American College of Foot and Ankle Surgeons: Tarsal Tunnel Syndrome

    2026 · Professional society clinical information

    Online page checked October 2026; year records verification. Plantar burning, tingling and numbness require nerve assessment. Does not attribute these symptoms to intrinsic muscle trigger points.