Skip to main content
Atlas · Hip

Piriformis

The piriformis is one of several small muscles deep in the buttock that help control hip rotation. It can be tender with buttock pain, but pain traveling down the leg deserves a hip, back and nerve assessment. A piriformis trigger point and sciatic nerve entrapment are different clinical possibilities and can coexist.

Piriformis
Body region
Hip
Trigger points
4
documented in this muscle
Common symptoms
4
patterns cataloged
Contributors
4
Factors to assess

Muscle overview

Symptoms and first steps

Practical first steps

  • Remove hard objects from back pockets and change sitting position before symptoms build.
  • Use brief comfortable walks; temporarily reduce the specific hills, pace or duration that flare symptoms.
  • Choose gentle hip movement only if it stays local and comfortable. Avoid forcing figure-four stretches or pressing a hard ball into the deep buttock.

When to seek assessment

  • Seek emergency care for new bladder retention or loss of control, saddle numbness, or rapidly progressive leg weakness. New foot drop or persistent numbness needs prompt assessment.
  • Arrange assessment for persistent radiating pain, loss of sensation, significant sitting limitation or symptoms after a fall. Fever or inability to bear weight needs urgent evaluation.

Active and seated piriformis tests assess a possible deep gluteal sciatic-nerve problem. Neither test diagnoses a trigger point, and a normal lumbar scan does not automatically identify the piriformis as the cause.

Examination, palpation and treatment evidence

Illustrated overview

Piriformis

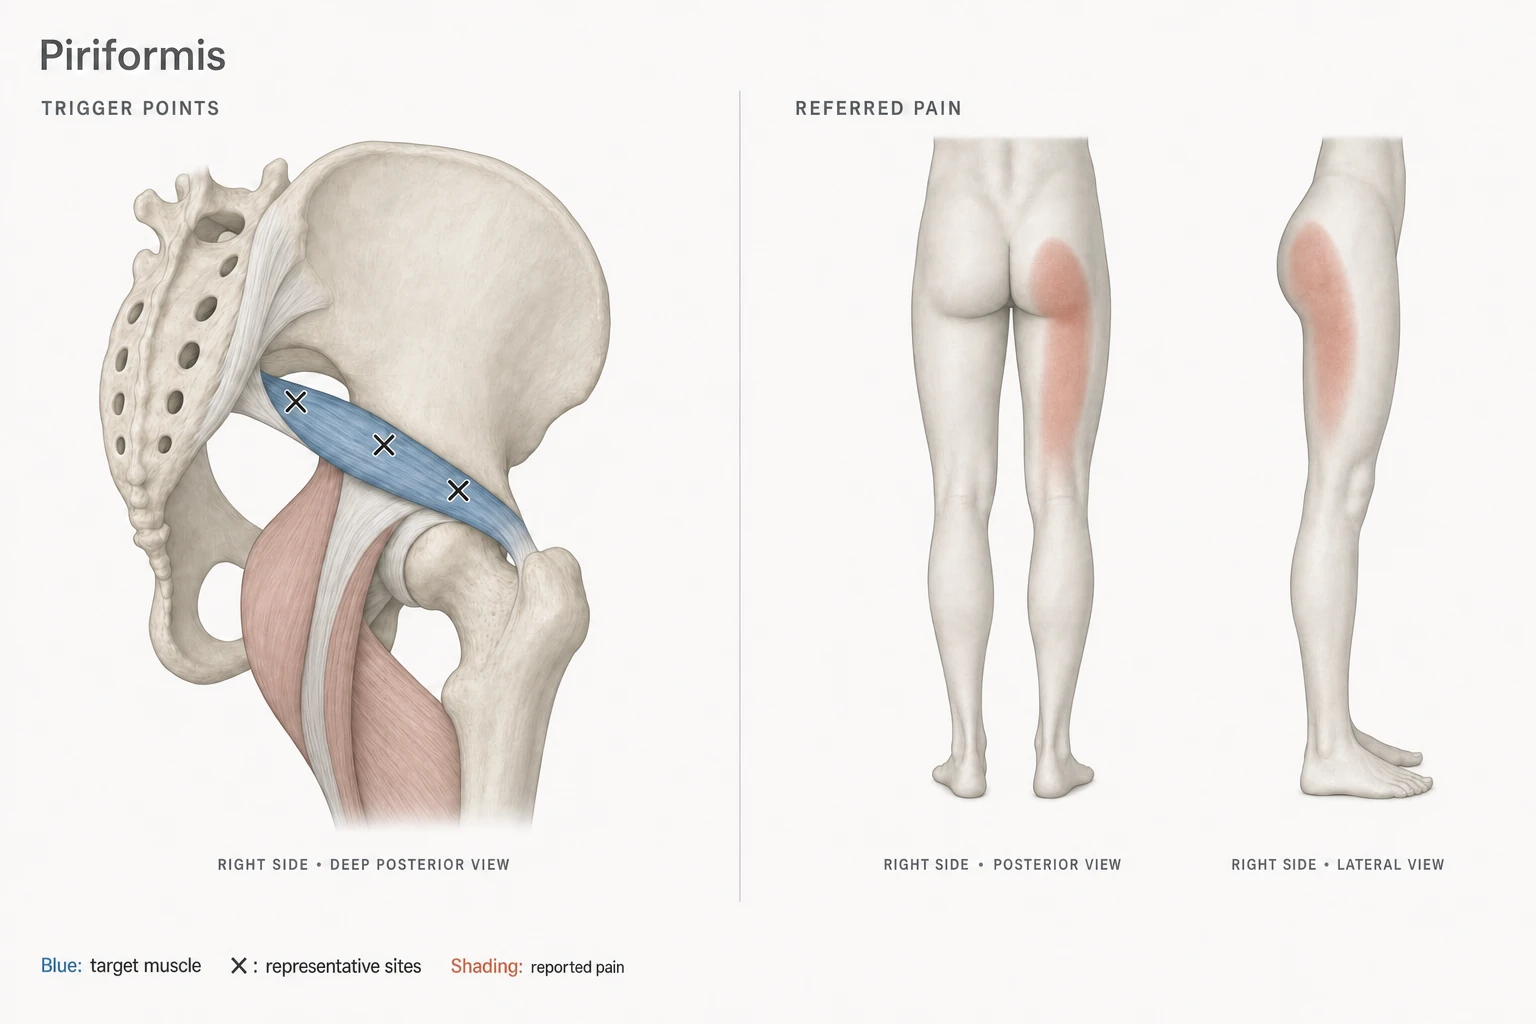
Blue highlights the muscle. Crosses mark representative trigger-point sites; shaded areas show possible referred pain. These examples do not correspond one-to-one with the numbered points below. Patterns vary and cannot diagnose the cause of pain.

Illustrated overview

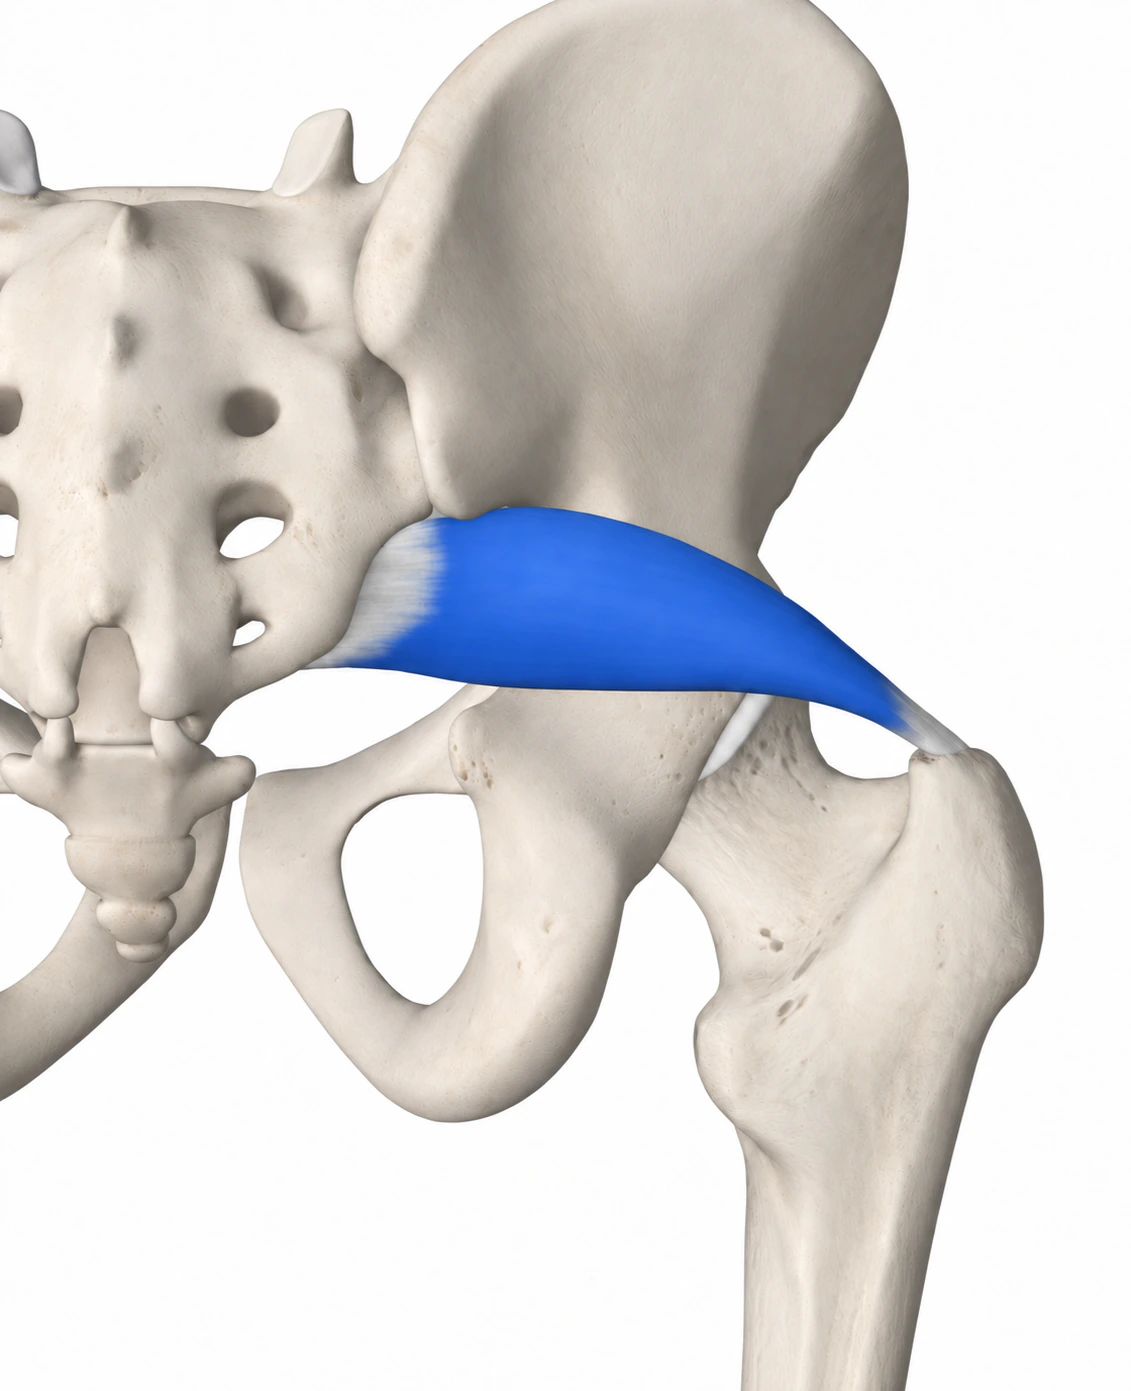
Piriformis · Anatomy 1

Anatomical view of the illustrated muscle.

Open full-size image

Trigger points

1. TrP1

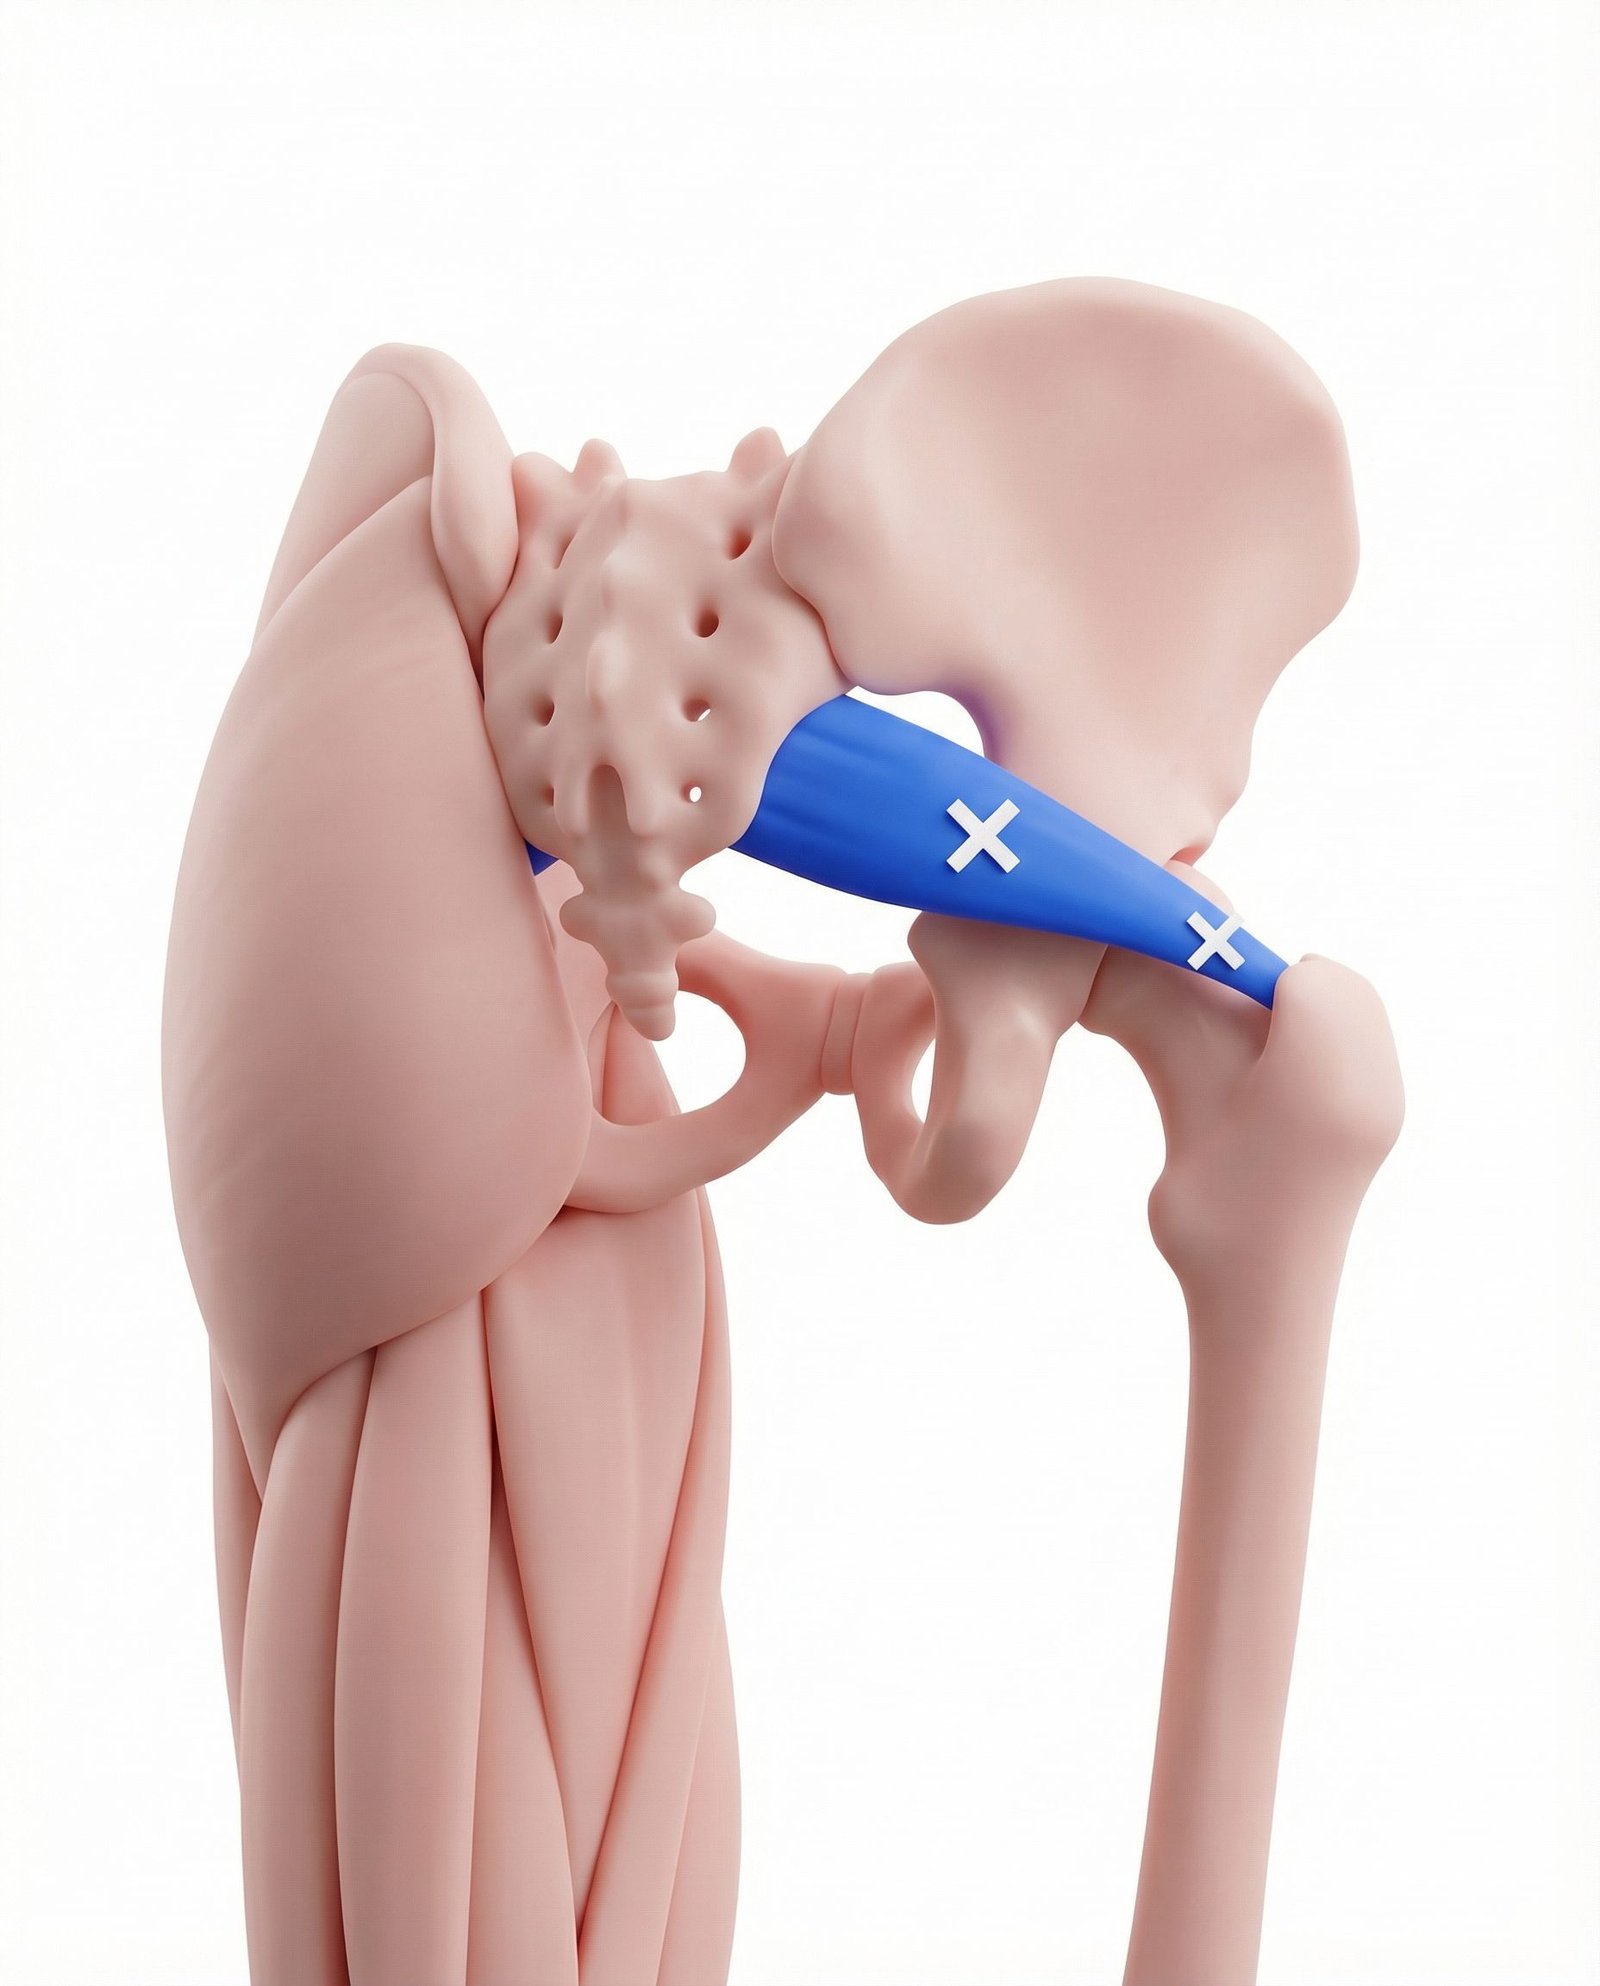
Location. Deep buttock, near sciatic nerve

Trigger point map
Piriformis — Trigger point mapOpen full-size image

Shared muscle diagram; it may show several trigger points.

Referred pain map
Piriformis — Referred pain mapOpen full-size image

Regional muscle reference; this is not an individual map of the selected numbered trigger point.

Pain referral. Buttock, back of thigh, calf

Pain Pattern

  • Buttock
  • Back of thigh
  • Calf
  • Lower back
  • Hip

What This Pain Feels Like

Deep buttock ache, often aggravated by prolonged sitting or hip rotation. Some people describe pain spreading into the posterior thigh; record accompanying sensory changes separately.

What Patients Report

  • Deep buttock pain
  • Pain with prolonged sitting
  • Discomfort during walking or hip rotation
  • Leg symptoms accompanying buttock pain

What Makes It Worse

  • Sitting
  • Running
  • Climbing stairs
  • Hip internal rotation
  • Prolonged sitting
  • Driving
Browse related exercises (4)

Symptoms patients report

Deep buttock ache May be noticed during sitting, driving or getting out of a chair; the same complaint occurs with several posterior hip conditions.

Pain with hip rotation Turning on the planted leg or bringing the knee across the body may reproduce symptoms; this is not specific to piriformis.

Reduced sitting tolerance Record how long sitting is comfortable and whether changing position or a short walk helps.

Pain spreading into the leg Aching can be referred, while persistent burning, numbness or weakness warrants a nerve examination rather than assuming a muscle knot.

Contributors to assess

A recent increase in hip loading More hills, running, climbing or unfamiliar rotation may coincide with symptoms. The load history guides rehabilitation but does not establish a trigger-point mechanism.

Long uninterrupted sitting Sitting may provoke the region; changing seat pressure and movement breaks can identify manageable aggravators.

A fall or previous hip procedure Trauma, postoperative changes and deep gluteal scarring can affect several structures and merit assessment.

Concurrent back or hip symptoms Lumbar, hip-joint and hamstring problems may contribute to the same complaint; apparent pelvic asymmetry alone is not an explanation.

For clinicians and supervised training

Clinical reference

Use the map to orient the examination; record the actual familiar pain distribution alongside movement, loading and neurological findings.

Anatomy and palpation

Anatomical relationships

Piriformis runs from the anterior sacrum through the greater sciatic foramen to the upper greater trochanter. Gluteus maximus overlies it. It assists external rotation of an extended hip and abduction of a flexed hip; its action changes with hip position.[6][10][11]

  • Sacrum provides the medial reference, but the anterior sacral origin cannot be directly palpated through the buttock.
  • The greater trochanter is the bony prominence on the outer upper femur; the tendon approaches its superior aspect.
  • The sit bone marks the proximal hamstring region below, not the piriformis insertion.

Nearby structures. The sciatic nerve usually exits below piriformis, with anatomical variants. Other deep rotators, proximal hamstrings and gluteal vessels are close; surface tenderness cannot identify a safe deep needle or pressure path.

Palpation

Patient position. Clinician examination with consent, draping and the patient side-lying or prone with the hip supported and gluteus maximus relaxed.

Find the landmarks

  • Identify sacrum, greater trochanter and ischial tuberosity before examining soft tissue.
  • Use the projected sacrum-to-superior-trochanter course to orient regional palpation, not a fixed trigger-point coordinate.

Examination sequence

  1. Begin with broad light contact, then graded fingertip pressure while asking whether symptoms are familiar or merely pressure discomfort.
  2. Compare the gluteal region with the hamstring origin and lateral hip. Brief gentle resisted rotation can help orient the examination but cannot isolate piriformis through the overlying muscles.

Document the findings

  • Document the location, local versus spreading sensation and recognition of the usual complaint.
  • A reliably felt sensitive band with familiar referral can support a myofascial hypothesis; the muscle depth limits confidence in isolating such a band.

Limits and precautions

  • Do not chase electrical pain or press through tingling. Stop the maneuver and assess neural symptoms.
  • Deep body-weight ball compression between the sit bone and greater trochanter can load the sciatic-nerve region and is not recommended.
  • Palpation alone cannot distinguish entrapment, muscle tenderness, tendon disease or referred lumbar pain.
[5][11][10]

Examination and tests

3

Active piriformis test[12][11]

Provoke symptoms associated with possible sciatic nerve entrapment in the deep gluteal space.

Position
Side-lying with symptomatic side uppermost, hip and knee flexed and heel supported on the examination table.
Technique
The clinician monitors the deep gluteal region while the patient presses the heel into the table and abducts and externally rotates the hip against gentle resistance.
Positive finding
Reproduction of the familiar deep posterior hip or buttock complaint.
Interpretation
Adds evidence to a deep gluteal assessment when consistent with the history and other findings.
Limitations
The combined active and seated tests had 91% sensitivity and 80% specificity in 33 surgically selected patients. These estimates concern endoscopic nerve entrapment, not trigger points or an unselected primary-care population.

Seated piriformis stretch test[12][11]

Assess posterior hip symptom provocation during a combined hip and neural loading maneuver.

Position
Seated with hip flexed to approximately 90 degrees; clinician-supported leg.
Technique
The clinician gradually extends the knee and guides the hip into adduction and internal rotation while monitoring the posterior gluteal region. Stop at symptom reproduction rather than forcing range.
Positive finding
The familiar posterior buttock pain is recreated; document any distal nerve symptoms separately.
Interpretation
Interpret with the active test, lumbar examination and differential findings.
Limitations
This maneuver also loads neural and adjacent rotator tissues. It is not the same as a home figure-four stretch and does not establish a trigger-point diagnosis.

Lumbar movement, neurological screen and straight-leg raise[8][12][9]

Look for a lumbar or neural explanation before attributing radiating pain to the buttock muscle.

Position
Standing for comfortable lumbar movements; seated or supine for strength, sensation and reflex examination, then supine for leg raise.
Technique
A clinician compares lower-limb strength, sensation and reflexes, observes symptom response to lumbar movement, then gently elevates the straight leg and records familiar radiating symptoms.
Positive finding
Concordant radiating symptoms, objective sensory/reflex/strength changes, or a clear change in leg symptoms with lumbar movement.
Interpretation
A coherent neurological pattern shifts the assessment toward nerve involvement and guides further investigation.
Limitations
A straight-leg raise alone cannot localize nerve irritation to the spine versus buttock. A negative test does not rule out deep gluteal entrapment.

Distinguishing other causes

Lumbar radiculopathy[9][8]

Findings that matter. Radiating leg symptoms with dermatomal sensory change, reflex asymmetry or myotomal weakness; back movements may reproduce or change symptoms.

Next step. Perform a neurological and lumbar examination; urgent escalation for progressive deficit or cauda equina features. Imaging is selected when it changes management.

Proximal hamstring tendinopathy[7]

Findings that matter. Pain is concentrated at the sit bone and aggravated by running or resisted knee flexion, especially with hip flexion.

Next step. Examine the hamstring origin and graded tendon loading before prescribing piriformis stretching or pressure.

Hip-joint disease[7]

Findings that matter. Groin-dominant pain, catching, reduced passive hip rotation or difficulty putting on shoes suggests a joint contribution.

Next step. Assess passive hip range and weight-bearing function; obtain medical assessment when limitation is substantial or traumatic.

Other deep gluteal entrapment[11]

Findings that matter. Persistent sitting-related neural symptoms can involve fibrous bands, other rotators, hamstring-related structures or a mass.

Next step. A specialist may consider targeted imaging or electrodiagnostic assessment if the examination supports this; a positive piriformis test does not identify the precise compressor.

Treatment selection and progression

Clinician-delivered care

Sciatic nerve hydrodissection for selected deep gluteal syndrome[1]

Consider when. Persistent symptoms attributed to sciatic entrapment in the deep gluteal space after lumbar, hip and tendon assessment.

A specialist uses real-time ultrasound to separate tissue around the sciatic nerve with fluid. The target is perineural tissue; isolated piriformis tenderness is insufficient to select this procedure.

Dose and review
The case series used a mixed injectate and repeated treatments about three weeks apart. It does not establish a required number of injections or a standard formulation.
Progression
Compare sitting tolerance, radiating pain and neurological findings after the initial treatment before considering repetition.
Stop or reassess
New weakness, sensory loss, expanding swelling or infection signs require prompt assessment.
Evidence and limits
In 53 patients, 62.3% reported at least 50% pain reduction at final follow-up, which ranged from 3 to 19 months. There was no control group, and drug and procedure effects could not be separated. This remains an early-evidence specialist option.

Clinician-delivered care

Ultrasound-assisted radial shockwave for persistent piriformis syndrome[2]

Consider when. A clinically assessed piriformis syndrome with ongoing sitting or walking limitation; may suit someone preferring a procedure without a needle.

A clinician localizes the deep piriformis and adjacent sciatic nerve with ultrasound, then selects a radial treatment target and tolerable exposure. Continue an individualized movement program.

Dose and review
The 2026 comparison tested three weekly sessions alongside stretching. This is a study course; its inconsistent device-unit reporting is unsuitable for a treatment prescription.
Progression
Record sitting tolerance, walking and leg symptoms before treatment, then review at about one month and again if benefit persists.
Stop or reassess
Reassess new radiating neurological symptoms or a persistent flare before further treatment.
Evidence and limits
Among 48 randomized patients (44 completed), DN and radial ESWT groups improved in pain, back disability and lower-limb function at 1 and 3 months. No between-group difference was found; without sham or an equivalence design this does not prove equal efficacy.

Clinician-delivered care

Specialist botulinum toxin discussion for persistent piriformis syndrome[3][4]

Consider when. Substantial sitting or walking limitation despite appropriate care, with a specialist-supported piriformis-related pain or entrapment diagnosis.

Discuss guided intramuscular treatment, formulation-specific effects and alternatives. Review baseline hip strength and neurological findings; a tender atlas point alone is insufficient selection.

Dose and review
One treatment followed by review; drug units are formulation-specific and no universal dose or repeat schedule is established here.
Progression
Compare pain with sitting and walking over the following weeks; consider further treatment only after meaningful functional benefit and review of weakness.
Stop or reassess
New weakness, altered gait, swallowing or breathing difficulty needs medical assessment; revisit diagnosis after absent benefit.
Evidence and limits
A selected 56-person trial found greater pain improvement with incobotulinumtoxinA plus PT than saline plus PT at 2–12 weeks. An 84-person active comparison favored toxin at 6 months but had no sham and baseline disability imbalance. These findings do not predict response in ordinary buttock myalgia.

Self-care and activity

Adjust sitting pressure and activity dose[11]

Consider when. Sitting-sensitive buttock pain without urgent neurological features.

Try a comfortable seat cushion, remove back-pocket objects and alternate sitting with short walks. Temporarily reduce the particular running or climbing exposure that reproduces symptoms.

Dose and review
Example: take a brief movement break before your usual symptom-onset time; the interval is individualized, not a validated piriformis dose.
Progression
Extend comfortable sitting or walking in small steps after repeated tolerable days.
Stop or reassess
Do not continue through spreading numbness, increasing leg pain or weakness; obtain assessment.
Evidence and limits
Conservative load modification is described in deep gluteal care. Its isolated effect has not been established in strong piriformis-specific trials.

Exercise and rehabilitation

Restore tolerable hip strength[7][11]

Consider when. Local load-related buttock discomfort once a clinician has considered hip, lumbar and neural causes.

Begin with a small bridge: lie on your back, knees bent, lift the pelvis only as far as comfortable and lower slowly. If tolerated, a clinician can add low-load hip rotation or step work matched to your provoking activity.

Dose and review
Example: 1 set of 6–8 bridges on alternate days. This is extrapolated regional rehabilitation, not a trial-validated piriformis protocol.
Progression
Build comfortable repetitions before resistance or single-leg demands; use next-day symptoms and sitting tolerance to guide changes.
Stop or reassess
Stop for radiating electrical symptoms, sharp groin pain or accumulating pain the next morning.
Evidence and limits
General hip conditioning is clinically reasonable, but this exercise does not selectively isolate piriformis or demonstrate that another muscle was compensating.

Exercise and rehabilitation

Use symptom-guided hip mobility[11]

Consider when. A measured hip movement limitation with local stiffness and no neural symptom provocation.

With your back supported and knees bent, explore a small comfortable hip rotation arc. A clinician may trial a gentle buttock stretch only when it improves a relevant movement; do not push the knee or pull into leg symptoms.

Dose and review
Example: 5 slow movements once daily, with no end-range hold initially. This is an individualized regional option, not a proven piriformis stretch dose.
Progression
Increase range only when the movement and subsequent sitting or walking remain comfortable.
Stop or reassess
Stop if symptoms spread farther down the leg or numbness appears; stretching an irritable nerve can worsen symptoms.
Evidence and limits
Stretching is used in conservative care, but the best position and dose are uncertain and it is not suitable for every posterior hip presentation.

Clinician-delivered care

Consider clinician-delivered ultrasound-guided dry needling[13][2]

Consider when. Persistent assessed piriformis-region pain when conservative care is insufficient and the patient prefers a time-limited adjunct.

A qualified clinician discusses bleeding, infection and sciatic nerve injury risks, reviews contraindications and uses ultrasound guidance; no self-needling or surface-coordinate needle instructions.

Dose and review
A small trial used three sessions; this describes the research exposure, not a recommended universal course.
Progression
Continue only if a predefined activity such as sitting or walking improves; pair any relief with active rehabilitation.
Stop or reassess
New neurological symptoms, marked persistent postprocedure pain or infection signs require reassessment.
Evidence and limits
A 32-person waitlist-controlled trial favored DN by about 2.16 pain-scale points at one week. In 2026, 48 patients were randomized to DN or radial ESWT, with stretching in both arms; 44 completed and both groups improved at 1 and 3 months without a clear between-group difference. Neither trial establishes superiority over sham or durable benefit beyond its follow-up.

Clinician-delivered care

Discuss an image-guided injection in selected persistent cases[14]

Consider when. A specialist-supported posterior hip diagnosis with persistent disability after a reasonable active-care trial.

Discuss the aim of an image-guided local-anesthetic injection and its alternatives. Drug selection and procedure planning belong to the treating clinician; temporary relief alone is not proof of a specific trigger point.

Dose and review
Individual medical decision; no drug dose or routine repeat series is recommended here.
Progression
Judge both duration of relief and change in a chosen task before considering any further procedure.
Stop or reassess
Reconsider the diagnosis after absent or fleeting benefit; urgently report new weakness, numbness, fever or severe worsening.
Evidence and limits
Of 50 randomized patients, 47 injection responders were retained as diagnosed piriformis syndrome. Lidocaine alone and lidocaine plus corticosteroid produced similar pain and activity outcomes at 1 week, 1 month and 3 months. Response-based selection and lack of sham limit efficacy and diagnostic claims; steroid added no clear benefit.
Reassessment and follow-up

  • Record comfortable sitting duration and a repeatable flat walking route before treatment; compare under similar conditions.
  • Track local buttock pain separately from the farthest extent of leg pain, numbness and any weakness.
  • Repeat the relevant hip movement or resisted test without forcing symptoms; an immediate tenderness change alone is insufficient.
  • If active care fails to improve function or neural findings emerge, revisit lumbar, hamstring, hip-joint and other deep gluteal causes rather than escalating pressure.

Evidence and sources

  1. Yen et al. Ultrasound-guided sciatic nerve hydrodissection in deep gluteal syndrome

    2024 · Uncontrolled case series

    53 patients followed for 3–19 months. A mixed dextrose/lidocaine/steroid injectate and absence of a comparator prevent attribution to hydrodissection alone.

  2. Dede et al. Extracorporeal shock wave therapy versus dry needling for piriformis syndrome

    2026 · Randomized clinical trial

    48 randomized, 44 completed; three weekly treatments plus stretching in both arms; 1- and 3-month follow-up. Full text describes ultrasound-assisted radial ESWT. No sham or equivalence design; inconsistent device units are not reproduced.

  3. Fishman et al. Electrophysiologically identified piriformis syndrome is successfully treated with incobotulinum toxin A and physical therapy

    2017 · Randomized clinical trial

    56 selected participants with FAIR-position H-reflex delay and normal paraspinal EMG; incobotulinumtoxinA plus PT versus saline plus PT. Pain benefit at 2–12 weeks; not a trial of isolated buttock tenderness.

  4. Elsawy et al. Efficacy of Ultrasound-Guided Injection of Botulinum Toxin, Ozone, and Lidocaine in Piriformis Syndrome

    2023 · Randomized clinical trial

    84 participants, 28 per arm; toxin, lidocaine or ozone, no sham. Lidocaine/ozone favored at 1 month, toxin at 6 months; baseline ODI imbalance limits inference. Ozone is a comparator, not a recommendation.

  5. International Consensus on Diagnostic Criteria and Clinical Considerations of Myofascial Trigger Points: A Delphi Study

    2018 · Expert Delphi consensus

    Expert criteria and familiar symptom recognition; no diagnostic gold standard or fixed referral map.

  6. Anatomy, Bony Pelvis and Lower Limb, Hip

    2023 · Clinical anatomy reference

    Attachments, muscle relationships and regional examination; anatomy does not establish a pain generator.

  7. Hip Pain in Adults: Evaluation and Differential Diagnosis

    2021 · Professional clinical review

    Regional hip, lumbar and posterior buttock differential; examination findings must be interpreted together.

  8. Approach to Musculoskeletal Examination

    2021 · Clinical examination textbook

    Regional examination techniques; general movement and strength findings are not trigger-point diagnostic tests.

  9. Low back pain and sciatica in over 16s: assessment and management

    2020 · Clinical practice guideline

    Assessment, continued activity, selective imaging and manual therapy within an exercise package.

  10. Piriformis muscle: clinical anatomy and consideration of the piriformis syndrome

    2007 · Cadaveric anatomy study

    112 specimens; attachment and tendon variation, not evidence that an anatomical variant causes symptoms.

  11. Deep gluteal syndrome

    2015 · Specialist clinical review

    Examination technique, differential and conservative-care context; lower certainty than comparative treatment trials.

  12. Diagnostic accuracy of clinical tests for sciatic nerve entrapment in the gluteal region

    2014 · Diagnostic accuracy study

    33 selected patients; endoscopic nerve-entrapment reference. Combined test estimates cannot diagnose trigger points.

  13. Ultrasound-guided dry needling decreases pain in patients with piriformis syndrome

    2019 · Randomized clinical trial

    32 participants, waitlist comparison, short follow-up; no long-term or sham-controlled claim.

  14. Piriformis Syndrome: Comparison of the Effectiveness of Local Anesthetic and Corticosteroid Injections: A Double-Blinded, Randomized Controlled Study

    2015 · Randomized clinical trial

    PMID 25794202; selected clinically diagnosed population, active comparison and response-based diagnostic definition limit generalization.

Associated Trigger Points